
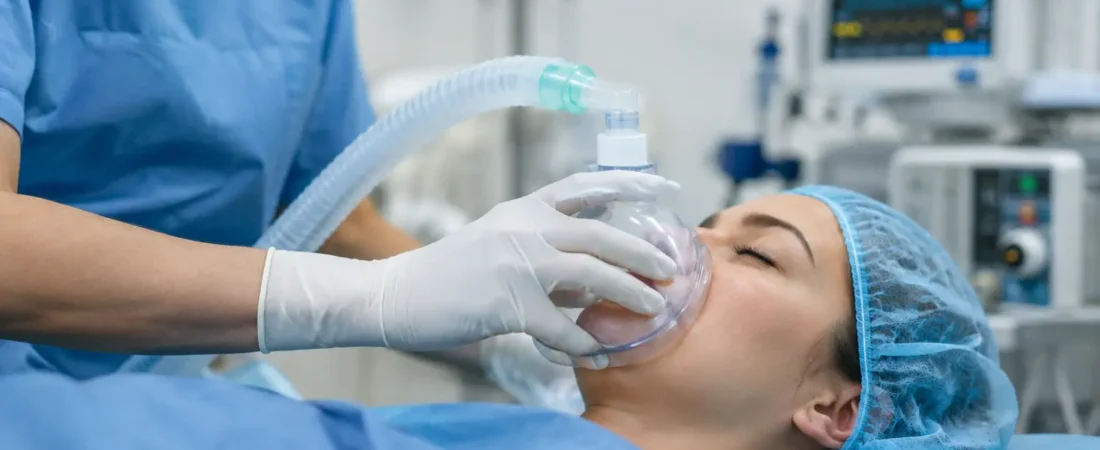
The operating room is designed to be a blank space in memory. A patient receives general anesthesia, loses consciousness, and later wakes in recovery with surgery already over. But in rare cases, the blank space contains fragments: a voice, pressure, panic, an inability to move, or the chilling certainty that something is happening nearby. How does anesthesia awareness happen when the entire purpose of general anesthesia is to prevent it?
The answer is not usually a single mistake or a simple case of a person being “not fully asleep.” Anesthesia is a moving target. The anesthesiology team must keep a patient unconscious, control pain, prevent movement, and preserve breathing, blood pressure, and other vital functions through a procedure that can change moment by moment. Sometimes those competing demands narrow the margin.
What anesthesia awareness actually means
Accidental awareness during general anesthesia usually refers to a patient becoming conscious enough during surgery to form an explicit memory afterward. This is different from dreaming under anesthesia, waking briefly as anesthesia is starting or ending, or receiving sedation for a procedure where some awareness is expected.
General anesthesia is not identical to natural sleep. It is a carefully managed drug-induced state with several separate components: unconsciousness, amnesia, pain control, and immobility. Different medications contribute to different parts of that state. A patient may have no memory of an operation even if the depth of anesthesia shifted briefly. Conversely, a person may later remember sound or fear without remembering pain.
The detail that makes these accounts especially distressing is paralysis. Many operations require neuromuscular blocking drugs, which temporarily prevent movement. These drugs do not create unconsciousness or relieve pain. They simply stop muscles from moving. If awareness occurs while paralysis is still active, a patient may be unable to signal that they are awake.
That scenario is rare, but its possibility explains why anesthesia awareness is taken seriously. The experience can be psychologically traumatic, particularly when it involves helplessness, pain, or a belief that death is imminent.
How does anesthesia awareness happen? The narrow margin problem
Anesthesia is adjusted constantly, not set once and forgotten. Clinicians consider the operation, the patient’s medical history, current medications, body response, blood pressure, oxygen levels, and the effects of surgical stimulation. In most cases, this monitoring and adjustment works exactly as intended. Awareness can occur when the usual balance is disrupted.
When deeper anesthesia could be dangerous
The most important trade-off is often hemodynamic stability. Anesthetic drugs can lower blood pressure and weaken the body’s cardiovascular response. During severe trauma, major bleeding, emergency cesarean delivery, or some heart procedures, giving a standard or deeper dose may create immediate danger.
In those situations, the team may need to use the lowest effective amount of anesthetic while treating the crisis itself. The priority is survival, but a lighter anesthetic state can raise the likelihood of awareness. This is not carelessness. It is a difficult clinical calculation made under conditions where every option carries risk.
When medication delivery changes
General anesthesia may be delivered through inhaled anesthetic gas, intravenous medication, or a combination of both. A disruption in delivery can matter. An IV line can infiltrate tissue instead of delivering medication into a vein. An infusion pump can malfunction. A vaporizer, breathing circuit, or medication connection can have a technical problem.
Modern anesthesia machines include alarms, checks, and safety systems designed to catch these events. Yet anesthesia is still a complex chain of people, equipment, physiology, and rapidly changing circumstances. Rare failures can occur anywhere in that chain.
When the patient needs more medication than expected
People do not respond to anesthetic medications in identical ways. Long-term use of opioids, sedatives, alcohol, or certain other substances can alter drug tolerance. Some medications may affect anesthetic requirements or how quickly drugs are metabolized. Severe anxiety, previous awareness, and certain genetic or physiologic differences may also be relevant to an anesthetic plan, although no single trait predicts awareness with certainty.
A patient who has had anesthesia awareness before should tell the anesthesiologist or nurse anesthetist before surgery. It does not mean it will happen again. It does mean the team can investigate the circumstances and plan with that history in view.
When surgery is urgent and information is incomplete
Elective surgery allows time for a careful preoperative history, medication review, and planning. Emergencies often do not. A critically injured patient may arrive with unknown medical conditions, an empty or full stomach, unstable blood pressure, and no one available to describe their medication use. Emergency anesthesia can be extraordinarily safe, but it operates under more constraints and less certainty.
The clues patients may remember
Reports of awareness vary. Some patients recall muffled conversation, music, instruments, or the sensation of a breathing tube. Others describe pressure, pulling, or an inability to breathe normally. Pain is possible, but not present in every case. Sometimes the memory is brief and hazy. Sometimes it is vivid enough to return as nightmares, flashbacks, panic, or avoidance of future medical care.
A troubling memory after surgery is worth reporting, even if it feels incomplete or strange. Memory formation around anesthesia is not always clean or chronological. A patient may have heard staff during emergence, had an intense dream, or experienced a period of genuine intraoperative awareness. The facts need to be examined rather than dismissed.
That distinction matters because awareness is often discovered only after the procedure. A person who cannot move cannot reliably alert the team in the moment. Afterward, a structured conversation can help identify what was recalled, when it may have occurred, whether pain was present, and what support is needed.
Why monitoring cannot read consciousness perfectly
During surgery, clinicians monitor far more than whether a patient appears asleep. Heart rate, blood pressure, oxygen level, exhaled anesthetic concentration, breathing parameters, temperature, and medication delivery all provide evidence. Physical responses such as tearing, sweating, movement, or changes in pulse can offer additional clues.
But none of these measurements is a perfect window into conscious experience. Blood pressure can rise because of surgical stimulation, illness, or medication effects. A paralyzed patient cannot move. Some patients show little outward response even when anesthetic depth is lighter than intended.
Brain-wave-based depth monitors may be used in selected circumstances, especially when intravenous anesthesia or elevated awareness risk is involved. These devices process electrical brain activity and produce a numerical estimate related to anesthetic effect. They can be useful, but they are not a lie detector for consciousness and do not eliminate risk. Their readings must be interpreted alongside the full clinical picture.
The unsettling truth is that consciousness itself remains difficult to measure. Medicine can track the body with extraordinary precision while still confronting uncertainty about the inner experience of the person on the operating table.
What anesthesia teams do to reduce the risk
Prevention begins before the first medication is given. The anesthesia professional reviews prior anesthetic experiences, current prescriptions, substance use, medical conditions, and the demands of the planned operation. If a patient describes past awareness, that history should be treated as clinically relevant, not embarrassing or inconvenient.
During the procedure, teams verify equipment, confirm medication delivery, watch anesthetic concentrations, and respond to changing vital signs. When muscle-paralyzing medication is used, careful management of anesthetic depth becomes even more critical because movement is no longer available as a warning sign. High-risk cases may call for additional planning, selected brain monitoring, or a deliberate discussion of the balance between anesthesia depth and cardiovascular safety.
There is no universal technique that erases awareness risk in every patient and every operation. The safer approach is individualized: identify the risk factors, anticipate the procedure’s demands, and maintain vigilance when physiology becomes unstable.
If you think it happened to you
Speak with the surgeon, anesthesiology department, primary care clinician, or a mental health professional experienced in trauma. Ask for a postoperative discussion and, if available, a review of the anesthesia record. Specific details can help: what you remember, whether you felt pain, whether you could move, and whether the memory seems connected to the beginning, middle, or end of surgery.
Do not assume you have to prove the experience before asking for help. The emotional aftermath can be real even while the timeline remains uncertain. Persistent nightmares, intrusive memories, insomnia, panic, or fear of medical care deserve attention. Trauma-focused counseling can be particularly helpful.
Before any future procedure, tell the anesthesia team exactly what you remember and how it affected you. That conversation turns an isolated, frightening memory into information the next team can use. The case may never yield a perfectly complete answer, but careful investigation is itself part of the care.